Medicare ACO & MIPS Registry for Independent Practices
Get paid for the care you already deliver.
Internal medicine physician
+$68K
Added in year one in our ACO, still independent


CMS-approved registry and Medicare ACO
4 of our quality measures approved by CMS
More than 100 practices across 12+ states
Run your numbers
See what our ACO could add to your practice
Independent practices usually leave four Medicare payments on the table. Set your practice size and watch them add up.
- 1Set your number of clinicians and weekly Medicare visits.
- 2Watch each payment, and the total, update as you go.
- 3On a 20-minute call, we calculate it from your real billing.
What our ACO could add to your practice
Set it to match your practice.
Clinicians
3clinicians
Medicare visits a week
45per clinician
Added revenue each year
$270,186
- Care management visitsWellness visits, care plans, monthly check-ins$105,000
- Office-visit bonusOpen to every practice, often never billed$82,593
- Extra bonus for ACO membersProposed for 2027, doubles the one above$82,593
Shared savings come on top, once a year.
Assumes $500K a year in Medicare billing per clinician. We calculate yours from your real billing.
How we calculate thisWhy the numbers differ
The same practice, paid two different ways
What stays the same
Your tax ID, your staff, your billing, and every clinical decision.
Reporting on your own
In the VBCA National ACO
Office-visit bonus
On your own: 16% extra on qualifying visits
In our ACO: 32% extra on qualifying visits, proposed for 2027
Care management
On your own: Wellness visits and care plans often go unbilled
In our ACO: Wellness visits, care plans, and monthly check-ins, run with our support
MIPS reporting
On your own: Your staff reports, with up to 9% of Medicare payments at risk
In our ACO: We report for the whole group in one submission
Shared savings
On your own: None
In our ACO: A share of the savings when the ACO spends less than Medicare's target. We carry the downside.
Patient cost data
On your own: Only your own claims
In our ACO: What each patient's care costs, across every provider they see
Our 2025 results
In its first year, our ACO spent $9.3 million less than Medicare expected
Medicare sets a spending target for every ACO. Coming in under it is how shared savings are earned, and the quality standard has to be met as well. We did both.
- below Medicare's spending target
- 7.1%
- Medicare's quality standard
- Met
- of first-year ACOs, historically
- Top 5%
- in MIPS penalties avoided for member practices
- $40M
Preliminary results. Medicare confirms the final numbers at reconciliation.
How our ACO worksWhy we exist
“When program complexity threatens business viability, it threatens healthcare access.”
Medicare's value-based programs weigh most on the practices with the fewest people to absorb them, and those are often the practices their communities depend on. Everything we build starts from that.
From our essay Business Viability Is Healthcare Access · Reviewed by Kristy Reinert, MD
49%
of solo clinicians were penalized under MIPS in the 2025 payment year. 29% took the maximum 9% cut, against 2% of clinicians overall.
Why VBCA
Policy meets engineering
- July 14Done
Medicare proposes its 2027 payment rules
We publish a plain-English breakdown of what it means for clients.
Read it - September 14Done
Public comments are due
We push back where a rule would penalize clinicians for things they can't control.
- NovemberUp next
Medicare finalizes the rules
Our team updates the measures, targets, and scoring in the platform.
- January 1
The 2027 year begins
Clients start the year already working to the final rules.
- January to March
2026 MIPS results are due
We submit for our registry clients and aim to finish in February.
20
Our founding team has written nearly 20 clinical quality measures
CMS invited us to introduce one of them, our SGLT2 measure for chronic kidney disease, nationwide in 2027.
Browse the measures
Kristy Reinert, MD
Co-founder and Chief Medical Officer
A Clinical Professor of Medicine at the University of Pennsylvania, she helped write our quality measures and advises our practices physician to physician.
Meet the teamThe platform
See what Medicare sees, before it scores you
Your cost scores, the patients driving your spending, and your quality reporting, all in one place. We run our own ACO on it, and we license it to other ACOs.
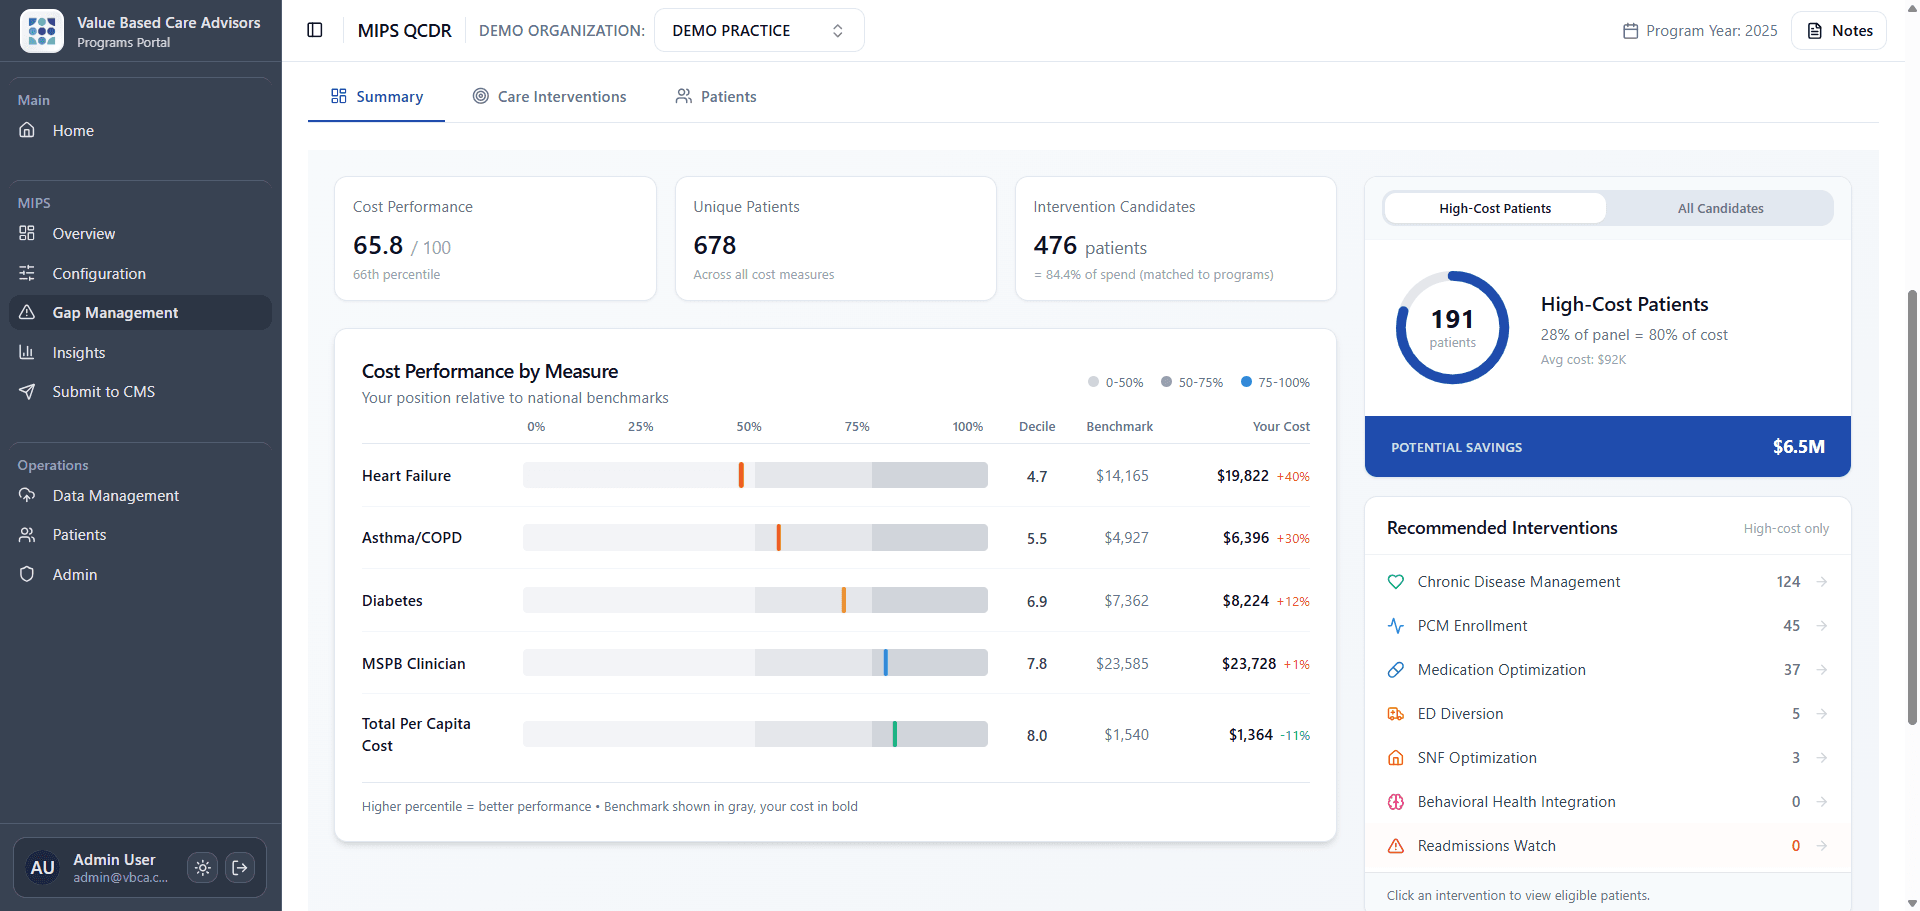
- Cost scores, benchmarkedEach condition's cost, next to the national average and your practice's rank.
- The patients driving spendingSee which patients account for the most cost, so you know where care management helps.
- Quality reporting, same placeYour quality measures next to your cost data, reported through our CMS-approved registry.
Demo practice shown.
Client results
What happens when your reporting catches up with the work you already do
Pain management practice
$850K
Penalized for years because their EMR only offered generic measures. We reported specialty measures from data already in their charts.
Before
9% penalty
After
Bonus
- $250KOrthopedic surgery groupRecovered by switching from generic to specialty measures
- $68KInternal medicine physicianAdded in year one in our ACO, still independent
- 11%Solo physicianRevenue swing once reporting came off his desk
- 148%Community practiceHigher score after leaving a manual reporting vendor

The switch from doing it ourselves to having their team handle it was the best operational decision we have ever made.
Ways to work with us
Start where you are today
- For independent practicesJoin our ACOShared savings, with the downside risk on usThe office-visit bonus, proposed at 32% for 2027Care management revenue, set up with your staff
- For any practice reporting MIPSMIPS reporting and strategySpecialty measures most EHRs don't offerYour score tracked all year, the way CMS will score itDirect submission through our CMS-approved registry
- For ACO leadersSoftware for your ACOAPP Plus quality reporting across all four collection typesContract analytics validated to within 0.03% of CMS's benchmarkBenchmark and savings down to every participant
Find out what your practice is leaving on the table
A free 20-minute call with the team that runs our ACO. We run the numbers on your real Medicare billing, not an estimate.
Book your call
Helpful to have: your specialty, number of clinicians, and last year's MIPS score if you know it.
Book the 20-minute callTalk to usOr email Support@VBCA.com